 The Unscripted Pharmacist
The book
Against the Current
Read the signals your CGM sends. Learn the numbers your checkup leaves out. Change what you do next.
Sense. Learn. Change.
The book and its free Lab
The book shows you why. The Lab shows you how, on your own body.

The book
The Lab · free
Hover a page to read it. Click to open.
On a glucose-lowering medication? Read the safety note first.
Same A1C. Different body.
A1C is your 3-month average glucose. Both people below pass as normal. Now look at insulin, your fat storage hormone.
PancreasWorking hard
PancreasHardly working
Both have normal blood sugar. Neither has diabetes. One is making 8 times more insulin to keep it there.
How long can a pancreas keep that up?

Diabetes "runs in the family." So do family dinners. Before you blame your genes, check your fasting insulin, the test that isn't on any panel.
Why is this hormone a secret?
- Measurable since 1960.
- Never part of how diabetes is diagnosed. Glucose only, then the A1C in 2010.
- Not on the screening lists. Medicare and the US screening guidelines name glucose and A1C. Not insulin.
- Not on any standard panel. Not the metabolic panel, the lipid panel or the blood count.
- Two lab companies, two different numbers. Results still are not standardized from one company to the next.
- Under $20. In most states you can order it yourself.
Insulin resistance was described in 1936: cells need more insulin to do the same job. Like a drug tolerance, it takes more to get the same effect. If you never measure it, you never have to explain it. How did we lose our way?
Let me show you what awareness can do.
The Unscripted Pharmacist
About me
I'm a pharmacist and a diabetes educator. Over 35 years inside the system. I taught the only diabetes education insurance would pay for. It failed. So I started measuring my own metabolism. I changed, and lost 50 pounds. My learning has made all the difference. I had to share it with everyone.

 2013

 Now
From Against the Current
Do you know your shadow?
Pick your glucose level.
Select your fasting insulin. See the shadow.
Dr. Joseph Kraft, a pathologist, found people who would pass a glucose test and still had high insulin. That's insulin resistance in broad daylight.
Supporting evidence
Normal glucose is not a quiet pancreas. In one database of 4,185 people with normal glucose, about half, 2,079, were making too much insulin anyway.
Crofts C, Schofield G, Zinn C, Wheldon M, Kraft J. Diabetes Res Clin Pract. 2016;118:50 to 57. PMID 27344544. Source
A second group gave 5,340 people the sugar drink and watched their blood for two hours. Every person in this part had normal glucose. Sorted by their insulin, the high-insulin people handled that drink the way people with new diabetes did. The insulin explained it. The glucose did not.
No organization has set a cutoff for that test. This is not a screening result and it does not sort anyone into a group. It is a signal the standard panel does not carry.
Wang Q, Jokelainen J, Auvinen J, et al. BMC Med. 2019;17(1):217. PMID 31779625. Source
On the assay: Staten M, Stern M, Miller W, Steffes M, Campbell S. Diabetes Care. 2010;33(1):205 to 6. PMID 20040676. Source
The numbers stay off the card unless you check the box.

Measure it
Glucose is what you see. Insulin is what you don't.
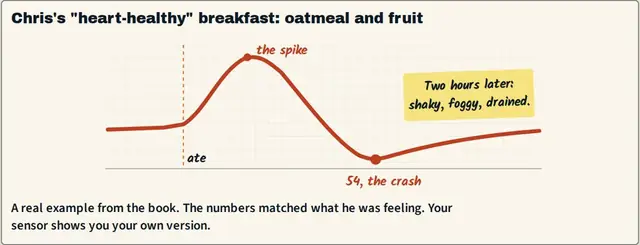
One CGM, one breakfast. Chris's oatmeal and fruit: the spike, then the crash two hours later.
Start here
Get a CGM
A CGM is the glucose sensor you wear on your arm. One blood draw is a photograph. A CGM is the movie. No prescription needed.
Then
Get your fasting insulin blood test
Your CGM shows glucose, not insulin. Most states let you order it yourself.
Then
Join The Unscripted Lab
The free CGM lab that goes with the book. The book shows you why. The Lab shows you how to see it in your own body.
On a GLP-1 or thinking about one?
That choice is yours and your prescriber's. I'm not here to talk you into it or out of it. A CGM shows you what your meals do, on the drug or off it. Know your numbers before you choose.
Is this book for you?
Where does high insulin flow?
Ten conditions linked to insulin resistance, each with its sources and the case against it. Plus the five-marker checklist you can run on your own numbers.

There is a way back
Metabolic disease is not your destiny.
It's a direction, and directions can change.
- The book. Against the Current. The class your checkup never taught.
- The Lab. Free. Put the book to work on your own body.
Read it. Measure it. Get off the medical merry-go-round.
On insulin, a sulfonylurea or an SGLT2 drug? Tap to read this first.
On a glucose-lowering medication? Read this first.
This is not for you if you have type 1 diabetes, kidney disease or advanced liver disease. Or if you are pregnant or breastfeeding, are under 18, or have a history of disordered eating or a hospital stay for eating.
Hunger or craving? A craving comes and goes. Hunger that stays for 30 minutes is your body telling you to eat.
A CGM can read low when it is not. Lying on it can show a false low. So can fasting and very low carb. Confirm a low with a finger stick. If you have symptoms, treat it first the way your prescriber told you, then confirm.
Get help now: a low with shaking or sweating. Confusion, or someone says you seem off. Vomiting, fruity breath, or deep fast breathing.
If food starts to feel scary, take it off and come back another time.
Taking a glucose-lowering medication?
On insulin or a sulfonylurea (glipizide, glyburide, glimepiride)? Those cause lows. Talk with your prescriber before you change how you eat, and follow their plan for a low.
On an SGLT2 inhibitor (empagliflozin, dapagliflozin, canagliflozin, ertugliflozin)? Talk with your prescriber before you cut carbs or fast. Low carbs and low fluids have both been linked to hospital stays on this drug while the glucose reading looked ordinary.
Get individual help from your provider.